
What is Trigeminal Neuralgia?
Trigeminal Neuralgia (TN) is a chronic facial pain disorder caused by irritation or compression of the trigeminal nerve - the fifth cranial nerve and the main sensory nerve of the face. It is widely regarded as one of the most painful conditions in medicine.
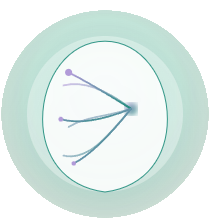
The nerve at the center of it all
The trigeminal nerve has three branches on each side of the face:
- V1 - Ophthalmic: forehead, scalp, and the area around the eye.
- V2 - Maxillary: cheek, upper lip, upper teeth and gums, side of the nose.
- V3 - Mandibular: lower jaw, lower lip, lower teeth and gums, part of the ear.
In classic TN, a blood vessel (usually the superior cerebellar artery) presses against the nerve where it exits the brainstem. Over time this contact wears away the nerve's protective myelin coating, making it misfire - sending bursts of agonizing pain in response to the lightest touch or sometimes nothing at all.
🎗️ Why teal?
Teal is the official international awareness color for Trigeminal Neuralgia. October 7th is International TN Awareness Day, when landmarks around the world light up in teal to honor those living with this condition.
The two types of TN
Doctors generally classify TN into two forms, though many patients experience features of both:
| Feature | Type 1 (Classical / TN1) | Type 2 (Atypical / TN2) |
|---|---|---|
| Pain quality | Sudden, electric-shock, stabbing | Constant burning, aching, throbbing |
| Duration | Seconds to about two minutes per attack | Hours or continuous |
| Pain-free periods | Often, between attacks | Rare - baseline pain almost always present |
| Response to carbamazepine | Usually excellent (diagnostic hallmark) | Partial, less reliable |
| Surgical outcomes | Generally very good (MVD especially) | More variable |
There are also secondary causes - multiple sclerosis, tumors, cysts, or structural abnormalities can produce "symptomatic" TN. An MRI is essential to rule these in or out.
Symptoms you may recognize
- Sudden, severe, lancinating pain usually on one side of the face.
- Pain that follows one or more branches of the trigeminal nerve.
- Attacks lasting seconds to minutes, often in clusters.
- A "trigger zone" - a small patch of skin that sets off attacks when touched.
- Pain-free intervals that may last days, weeks, or months (especially early on).
- Over time, remission periods often shrink and attacks become more frequent.
- Secondary consequences: weight loss, anxiety, depression, social isolation.
Common triggers
Even gentle, everyday actions can set off attacks. Many patients learn to live around their triggers:
- Light touch to the face - a kiss, a breeze, splashing water.
- Brushing teeth, flossing, chewing, swallowing.
- Talking, smiling, laughing.
- Shaving, applying makeup, washing the face.
- Cold wind or air conditioning.
- Vibration - walking on uneven ground, car rides.
How TN is diagnosed
There is no single blood test or scan for TN. Diagnosis is primarily clinical, based on the character of the pain, its distribution along the nerve, and its response to specific medications. Essential steps usually include:
- A thorough history: location, quality, triggers, duration of attacks.
- A neurological exam to look for sensory loss or motor deficits.
- A high-resolution MRI (ideally with FIESTA/CISS sequences) to look for vascular compression and rule out tumors or MS.
- A trial of carbamazepine or oxcarbazepine - dramatic relief strongly supports TN1.
Average time to correct diagnosis in the US is still measured in years, often with multiple unnecessary dental procedures along the way. Advocacy and awareness help shorten that journey.
Help change the story
If you or someone you love has TN, sharing accurate information is powerful. Many TN patients are first misdiagnosed with dental problems, TMJ, migraines, or sinus issues. Spreading awareness - especially among dentists and primary-care doctors - can shave years off someone's search for answers.